In the era of biohacking, podcasts, and medical advice served with a latte in 2026, many people start to think of phosphodiesterase type 5 inhibitors as “performance vitamins.” From a clinical standpoint, that idea is about as accurate as calling insulin a lifestyle supplement. The prescription-only status of Viagra and its generic equivalents is not a bureaucratic nuisance. It is a core safety protocol grounded in cardiovascular physiology, pharmacodynamics, and decades of post-marketing surveillance.
In this article, we break down why unsupervised sildenafil use represents a real medical risk and why the physician’s role in prescribing these molecules remains non-negotiable.
1. Cardiovascular Risk: Systemic Vasodilation Is Not a Trivial Matter
The primary reason sildenafil requires a prescription is embedded in its mechanism of action. Sildenafil inhibits phosphodiesterase type 5, leading to accumulation of cyclic guanosine monophosphate and relaxation of smooth muscle. That effect is not confined to the corpora cavernosa. Phosphodiesterase type 5 is also expressed throughout the systemic vasculature.
In a healthy adult male, a single 100 milligram dose of sildenafil typically lowers blood pressure by approximately 8/5 millimeters of mercury. In isolation, that drop is clinically insignificant. In patients with coronary artery disease, heart failure, or aortic stenosis, however, even modest hypotension can precipitate myocardial ischemia or hemodynamic instability (Goldstein et al., 2019).
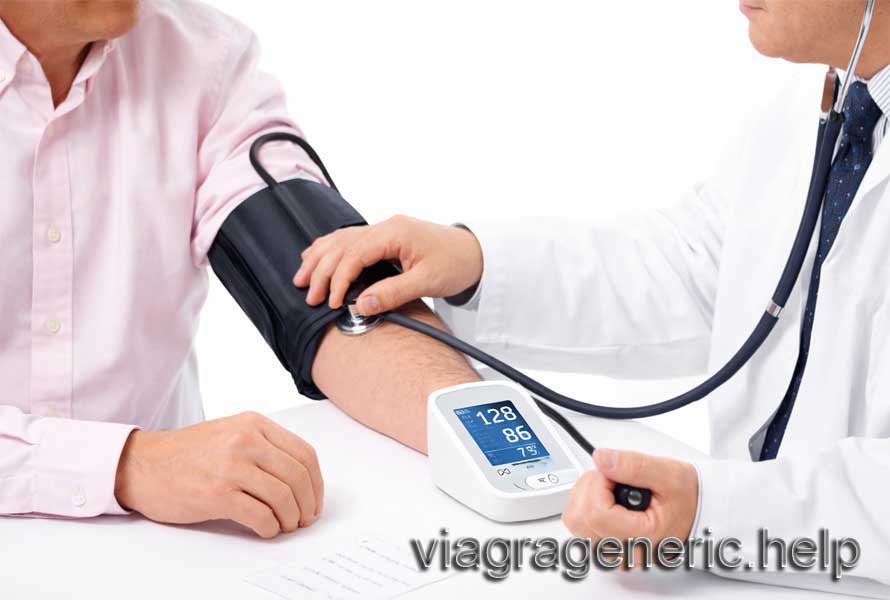
Only a physician can determine whether a patient’s cardiovascular system can tolerate not just the drug itself, but also the additional hemodynamic load associated with sexual activity. As we say in the clinic, the heart does not care whether the stress test is on a treadmill or in the bedroom.
2. Lethal Drug Interactions: When Pharmacology Turns Ruthless
Prescription oversight exists to prevent catastrophic combinations. The most dangerous interaction involves sildenafil and nitrates, including nitroglycerin and isosorbide derivatives.
The cascade is straightforward and unforgiving:
- Nitrates act as direct nitric oxide donors.
- Nitric oxide stimulates cyclic guanosine monophosphate production.
- Sildenafil blocks cyclic guanosine monophosphate degradation.
The result is an uncontrolled surge in cyclic guanosine monophosphate, leading to profound and sometimes irreversible hypotension, which can be fatal (Ghofrani et al., 2006).
Without medical supervision, patients may not realize that their anti-anginal medications or certain recreational substances, such as alkyl nitrites commonly known as “poppers,” belong to the nitrate class. From an emergency medicine perspective, this is not theoretical risk. It is a chart review waiting to happen.
3. Diagnostic Value: Erectile Dysfunction as an Early Warning Signal
From the standpoint of evidence-based medicine in 2026, erectile dysfunction is often the first clinical manifestation of systemic endothelial dysfunction. Penile arteries measure approximately 1 to 2 millimeters in diameter, whereas coronary arteries average 3 to 4 millimeters. Smaller vessels fail first.
Population data consistently demonstrate that erectile dysfunction precedes myocardial infarction or stroke by an average of three to five years (Montorsi et al., 2021). When a patient self-medicates with a generic sildenafil product, the symptom is masked. The underlying pathology—diabetes mellitus, atherosclerosis, metabolic syndrome, or hypogonadism—continues to progress unchecked.
Requiring a prescription ensures that the patient undergoes at least minimal diagnostic screening. In many cases, that screening is not about sexual performance. It is about survival.
4. Differential Diagnosis and Individualized Dosing
Erectile function is regulated by vascular integrity, hormonal balance, and neural signaling. In clinical practice, we routinely encounter patients who report that Viagra “does not work,” when the actual problem is androgen deficiency, hyperprolactinemia, or major depressive disorder.
Physicians individualize dosing based on comorbid conditions:
- 25 milligrams for patients with renal or hepatic impairment.
- 50 milligrams as the standard starting dose.
- 100 milligrams reserved for severe vasculogenic erectile dysfunction.
Unsupervised escalation to maximal dosing increases the incidence of adverse effects, including cyanopsia and severe headache (Lovallo, 2006). From a clinician’s perspective, this is avoidable harm.
5. Rare but Serious Complications
Certain conditions demand extreme caution. Priapism, defined as a painful erection lasting longer than four hours, is a urologic emergency. Without prompt intervention, it leads to irreversible fibrosis and permanent erectile dysfunction.
Prescription control also protects patients with inherited retinal degenerative disorders, in whom phosphodiesterase type 5 inhibitors significantly increase the risk of vision loss (Smith et al., 2025). These are not risks that should be discovered through trial and error.
6. Counterfeit Drugs and the Gray Market
A prescription is also a safeguard against counterfeit pharmaceuticals. According to World Health Organization data, Viagra is among the most frequently falsified medications globally. Products sold without a prescription on unregulated websites have been found to contain heavy metals, talc, or incorrect concentrations of active ingredients.
From a toxicology standpoint, buying sildenafil without a prescription is less like shopping and more like playing roulette with your liver.
Conclusion
The prescription status of Viagra reflects medicine’s obligation to patient safety. Erectile function is not an isolated event. It is a downstream marker of cardiovascular and endocrine health.
Seeking a prescription is not a sign of weakness. It is a rational, adult decision grounded in preventive medicine, longevity, and quality of life. If your heart is not cleared, nothing else matters.
References
- Ghofrani, H. A. et al. (2006). Sildenafil: from angina to erectile dysfunction to pulmonary hypertension and beyond. Nature Reviews Drug Discovery.
- Goldstein, I. et al. (2019). The Serendipitous Discovery of Sildenafil: 20 Years of Clinical Success. Sexual Medicine Reviews.
- Lovallo, J. (2006). PDE5 Inhibitors and the Retina: Understanding Visual Side Effects. Ophthalmology Reports.
- Montorsi, F. et al. (2021). Pharmacogenetics of PDE5 Inhibitors: Personalized Treatment of Erectile Dysfunction. European Urology Focus.
- Smith, B. P. et al. (2025). Erectile Dysfunction as a Cardiovascular Risk Predictor: A Decadal Review. Lancet Health.
- Viatris Medical Reports (2025). Safety Pharmacology of Sildenafil Citrate. Clinical Database.